

CJC-1295 and Ipamorelin: key takeaways
CJC-1295 and ipamorelin are research peptides that act on two different parts of the GH axis. This guide covers the evidence, reported practice amounts, reconstitution and the approval status as of September 2026.
- The common product is a 1:1 blend of 5 mg CJC-1295 without DAC and 5 mg ipamorelin per vial.
- Human studies used CJC-1295 with DAC as single injections or every 1 to 2 weeks (20 to 250 µg/kg, i.e. 1.4 to 17.5 mg at 70 kg) or intravenous ipamorelin. The blend and the no-DAC form have no controlled human study.
- In practice (reported use), 100 mcg of each peptide one to three times daily is the most frequently reported amount, which equals 6 units on a U-100 syringe per injection when 3 ml of solvent is used.
- After mixing, the supplier advises using the solution within about four weeks at 2 to 8 °C; no independent stability data are published.
Jump to the dosage chart, the reconstitution steps or the FAQ.
What is the CJC-1295 and Ipamorelin blend?
CJC-1295 and ipamorelin is a pairing of two GH-releasing peptides, usually CJC-1295 without DAC (Mod GRF 1-29) plus ipamorelin, often sold as a 1:1 blend such as 5 mg + 5 mg per vial.
CJC-1295 is a synthetic analogue of growth hormone-releasing hormone (GHRH), and ipamorelin is a pentapeptide that releases GH through the ghrelin (GHS) receptor. The combination usually appears as a lyophilized research product; the CJC-1295/Ipamorelin blend (5 mg + 5 mg) is one example of that format.
Naming is inconsistent. In the scientific literature "CJC-1295" usually means the long-acting form with DAC, while shops usually sell the form without DAC under that name. The FDA lists CJC-1295 and CJC-1295 DAC as two different, non-interchangeable substances (FDA briefing document, December 4, 2024).
What is CJC-1295 (the CJC peptide)?
CJC-1295 is a 29-amino-acid GHRH(1-29) analogue with four substitutions (D-Ala2, Gln8, Ala15, Leu27), and it exists in a form with a drug affinity complex (DAC) and a form without it. The DAC form carries a maleimidopropionamide-lysine (MPA-Lys) unit that binds serum albumin, which is why it is also described as CJC-1295 DAC; the form without DAC is widely known as Mod GRF 1-29 (Jette et al. 2005).
How do CJC-1295 and Ipamorelin work?
CJC-1295 activates the GHRH receptor and ipamorelin the ghrelin (GHS) receptor, so the pair is meant to stimulate GH release through two receptor classes.
Native GHRH is cut into an inactive fragment within minutes in plasma, and the D-Ala2 substitution slows that clearance (Frohman et al. 1986; Soule et al. 1994). In the DAC form, CJC-1295 binds serum albumin. After one subcutaneous injection of CJC-1295 with DAC, GH rose 2- to 10-fold for 6 days or longer, and IGF-1 rose 1.5- to 3-fold for 9 to 11 days. The pulsatile pattern of GH release was preserved; mainly the trough levels rose (about 7.5-fold) (Teichman et al. 2006; Ionescu and Frohman 2006).
Ipamorelin releases GH through the ghrelin receptor and was about as potent as GHRP-6 in rat pituitary cells (EC50 1.3 versus 2.2 nmol/l). In pigs it did not raise ACTH or cortisol above the level seen with GHRH, even at more than 200 times the ED50, but comparable human data are thin (Raun et al. 1998; FDA briefing document, October 29, 2024).
Why combine them? The idea rests on one 1990 study in 18 healthy men where a GHRP hexapeptide and GHRH(1-44) released GH synergistically. Neither ipamorelin nor CJC-1295 was tested there, and no controlled study has tested this specific blend (Bowers et al. 1990).
CJC-1295 with DAC vs without DAC (Mod GRF 1-29)
With DAC the estimated half-life is 5.8 to 8.1 days, and every human study used that form; without DAC there is no reported human half-life and no controlled human study.
The two forms are different substances and are not interchangeable. The FDA found no pharmacological studies for the form without DAC, and related GHRH fragments are degraded within minutes. A 2026 evidence review rates CJC-1295 with DAC as stage B (phase 1 and 2 data) and the form without DAC as stage D (no reviewed human studies) (Dominikowski et al. 2026).
CJC-1295 and Ipamorelin research and evidence
Human data cover three small CJC-1295-with-DAC studies in 63 healthy volunteers plus one phase 2 trial stopped in 2006, and intravenous ipamorelin in one PK study and two phase 2 trials; the blend and the no-DAC form have no controlled human study.
The three CJC-1295 studies enrolled 63 healthy volunteers (87 percent men, 73 percent received a single injection, doses 20 to 250 µg/kg). The phase 2 program in HIV-associated visceral obesity (NCT00267527) was terminated in 2006 without published results. Ipamorelin reached phase 2 twice: after bowel surgery (Beck et al. 2014) without proof of efficacy, and in a dose-finding trial (NCT01280344) whose results were never posted. No phase 3 program exists for either peptide.
Human studies at a glance
Three small studies tested CJC-1295 with DAC in healthy adults, and two phase 2 programs tested intravenous ipamorelin without proof of efficacy.
| Study (year) | Population | Compound and route | Duration | Result |
|---|---|---|---|---|
| Teichman 2006, Study 1 | healthy adults, part of the 63 | CJC-1295 with DAC s.c. | observation 28 or 49 days | GH 2- to 10-fold for 6 days or longer, IGF-1 1.5- to 3-fold for 9 to 11 days; IGF-1 above reference range only at 250 µg/kg; estimated half-life 5.8 to 8.1 days |
| Teichman 2006, Study 2 | 24 participants in four groups of six | CJC-1295 with DAC s.c. | observation 28 or 49 days | estimated half-life 5.4 to 9.2 days; IGF-1 above baseline for up to 28 days; tolerability best at 30 or 60 µg/kg; no serious adverse reactions |
| Ionescu and Frohman 2006 | 12 healthy men, 20 to 40 years | CJC-1295 with DAC s.c. | measured 1 week later | pulse frequency and amplitude unchanged, GH nadir 7.5-fold, mean GH +46 %, IGF-1 +45 %, no IGF-1 above the upper reference limit |
| Sackmann-Sala 2009 (re-analysis, not a separate study) | 11 men from the Ionescu 2006 cohort | CJC-1295 with DAC s.c. | single dose | proteomic analysis, no side-effect data |
| NCT00267527 (phase 2) | HIV-associated visceral obesity (n not reported consistently) | CJC-1295 with DAC s.c. vs placebo | 12 weeks | terminated in 2006, no published results; one death from acute myocardial infarction two hours after the week 11 dose |
| Gobburu 1999 | 48 healthy men | ipamorelin IV over 15 min | single dose | dose-proportional kinetics, terminal half-life 2 h, one GH peak at 0.67 h |
| Beck 2014 | 117 patients after bowel resection, 114 analyzed | ipamorelin IV | up to 7 days | no significant differences on primary and secondary endpoints; adverse events 87.5 % vs 94.8 % placebo |
| NCT01280344 (phase 2) | 320 participants | ipamorelin IV | completed May 2014 | registered as completed, no results posted |
Benefits and muscle growth: what has actually been studied?
No controlled study shows muscle growth or body-composition change from CJC-1295 and ipamorelin; the measured effects are GH and IGF-1 increases under CJC-1295 with DAC. Outcomes such as fat loss, sleep quality or recovery are not established in controlled studies, and muscle-growth claims are not supported by clinical data.
CJC-1295 and Ipamorelin dosage
The most commonly reported CJC-1295 and ipamorelin dose is 100 mcg of each peptide (6 units on a U-100 syringe with 3 ml in a 5 mg + 5 mg vial), one to three times daily; no dose is approved, and study doses used other forms.
This section separates study doses from reported use. Reported use means amounts that forums, supplier pages and clinic websites describe; they are not study doses and not recommendations from a health authority. The following sections cover the chart, what studies tested and what users report.
CJC-1295 and Ipamorelin dosage chart
The chart lists the patterns that appear in reported use, with syringe units calculated for a 5 mg + 5 mg vial mixed with 3 ml of bacteriostatic water.
| Schedule (reported use) | Per injection (each peptide) | Per day (each peptide) | Units on U-100 per injection (3 ml) |
|---|---|---|---|
| Entry, once daily in the evening for the first 2 weeks | 100 mcg | 100 mcg | 6 units |
| Once daily | 100 to 300 mcg | 100 to 300 mcg | 6 to 18 units |
| Twice daily, morning and before bed | 100 mcg | 200 mcg | 6 units |
| Three times daily (forum pattern) | 100 mcg | 300 mcg | 6 units |
Every draw from a 1:1 blend contains both peptides, so the per-injection amounts for CJC-1295 and ipamorelin are identical. Single forum reports go higher, up to 500 mcg of CJC-1295 without DAC plus 1 mg of ipamorelin per dose, and those are individual accounts rather than a pattern. For other vial sizes and solvent volumes, use the peptide dosage calculator.
CJC-1295 and Ipamorelin dosage in studies
Study doses were CJC-1295 with DAC 20 to 250 µg/kg subcutaneously (1.4 to 17.5 mg at 70 kg) or intravenous ipamorelin at about 3 to 100 µg/kg once and 0.03 mg/kg twice daily up to 0.06 mg/kg three times daily.
| Compound | Study or program | Dose | Schedule | Calculated at 70 kg |
|---|---|---|---|---|
| CJC-1295 with DAC | Teichman 2006, Study 1 | 30 to 250 µg/kg s.c. | single ascending doses | 2.1 to 17.5 mg per injection; best tolerated 30 or 60 µg/kg = 2.1 to 4.2 mg |
| CJC-1295 with DAC | Teichman 2006, Study 2 | 20 to 60 µg/kg s.c. | days 0 and 14 (30 or 60 µg/kg) or days 0, 7, 14 (20 or 30 µg/kg) | 1.4 to 4.2 mg per injection |
| CJC-1295 with DAC | Ionescu 2006 | 60 or 90 µg/kg s.c. | once | 4.2 to 6.3 mg |
| CJC-1295 with DAC | NCT00267527 (terminated) | 60 to 240 µg/kg s.c. | weekly with 3-week escalation | 4.2 to 16.8 mg |
| Ipamorelin | Gobburu 1999 | 4.21 to 140.45 nmol/kg IV over 15 min (about 3 to 100 µg/kg) | once | about 0.2 to 7 mg |
| Ipamorelin | Beck 2014 | 0.03 mg/kg IV twice daily | postoperative days 1 to 7 | 2.1 mg per infusion |
| Ipamorelin | NCT01280344 | 0.03 mg/kg twice daily, 0.06 mg/kg twice or three times daily IV | dose-finding arms | 2.1 and 4.2 mg per infusion |
| CJC-1295 without DAC and the blend | no study | no study dose | not studied | not studied |
Reported CJC-1295 and Ipamorelin dosing in practice
100 mcg of each peptide, one to three times daily, is the most frequently reported amount in practice (reported use).
| Source | Amount per peptide | Frequency | Amount per day | Cycle | Notes |
|---|---|---|---|---|---|
| TMuscle forum 2014 (1 report) | 100 mcg Mod GRF 1-29 plus 100 mcg ipamorelin | three times daily (morning, late afternoon, 1 h before bed) | 300 mcg each (calculated) | not specified | called a "saturation dose" by the user; parallel 3 IU GH |
| ExcelMale 2020 (2 reports) | 100 mcg each | three times daily, or once daily before bed fasted on 5 of 7 days | 300 mcg or 100 mcg each (calculated) | not specified | separate 5 mg vials, 3 ml BAC water, 6 units per 100 mcg |
| ExcelMale 2022 (1 report) | about 100 mcg Mod GRF 1-29 | not specified | not specified | not specified | 2 mg vial plus 2 ml = 1000 mcg/ml, 100 mcg = 10 units |
| AnabolicMinds 2022 (1 report) | 100 mcg each | three times daily | 300 mcg each (calculated) | not specified | single IGF-1 report with confounders (old baseline value, parallel testosterone, prior MK-677) |
| Peptide Critic 2026 (4 users) | 135 mcg each; or 500 mcg CJC without DAC plus 1 mg ipamorelin; or "300 mcg" per injection (split between peptides not stated); or 0.5 mg each | once to three times daily | 135 mcg each up to single reports of 500 mcg plus 1 mg | 5 days on and 2 days off; 12 to 14 weeks then 3 months off, or 12 weeks then 4 weeks off | wide, non-comparable span |
| Supplier guide and calculator (BergdorfBio) | CJC-1295 without DAC 100 to 200 mcg plus ipamorelin 200 to 300 mcg | twice daily (morning fasted, 30 to 60 min before bed); entry 100 mcg CJC in the evening for 2 weeks | CJC 200 to 400 mcg, ipamorelin 400 to 600 mcg (calculated) | 8 to 12 weeks on, 4 weeks off | ipamorelin without titration |
| Dosing site PeptideDosages.com (updated September 20, 2026) | 100 to 300 mcg each | once daily | 100 to 300 mcg each | start 100 mcg, plus about 50 mcg every 1 to 2 weeks | 10 mg blend mixed with 3 ml bacteriostatic water; for syringe units, use the calculator below |
| Review Dominikowski 2026 (forum-derived) | CJC-1295 without DAC 100 to 200 mcg; ipamorelin 200 to 300 mcg; CJC with DAC 1 to 2 mg per week | one to twice daily; two to three times daily; one to two injections per week | CJC 100 to 400 mcg, ipamorelin 400 to 900 mcg (calculated) | 8 to 16 weeks on, 4 to 6 weeks off | summary of forum-reported practice |
| FDA scan of US clinic websites 2024 | CJC-1295 100 mcg per week to 100 to 400 mcg per day; fitness range 250 mcg per day to 100 to 200 mcg two to three times daily | mostly evenings, some 5 of 7 evenings | as listed | not specified | which CJC form is meant is usually not stated |
CJC-1295 and Ipamorelin dosage per day and calculator
Per day, the common pattern adds up to 100 to 300 mcg of each peptide, or 200 to 600 mcg of total peptide; the higher single reports are in the practice table above.
In the CJC-1295 and Ipamorelin dosage calculator, for a 5 mg + 5 mg blend vial with 3 ml of bacteriostatic water, enter the content of one component (5 mg) as the vial size, 3 ml as the water volume and 0.1 mg (100 mcg) as the dose. The step-by-step math is in the reconstitution section below. The same calculator handles other vial sizes, solvent volumes and schedules.
When to take CJC-1295 and Ipamorelin: morning, before bed or fasted
Reported timing is either one injection in the evening or a split schedule in the morning and before bed, and no study has compared schedules or tested fasting.
The patterns come from reported use: one user injects once daily before bed, fasted, on 5 of 7 days; the supplier guide describes an entry of 100 mcg in the evening and a classic split of morning (fasted) and 30 to 60 minutes before bed; forum reports add early morning, late afternoon and one hour before sleep, or after training and before bed. Whether fasting changes the GH response to this combination has not been studied.
How to reconstitute the CJC-1295 and Ipamorelin blend
Add 3 ml of bacteriostatic water to a 5 mg plus 5 mg vial to get 1.667 mg/ml per peptide, so 100 mcg of each equals 6 units on a U-100 syringe.
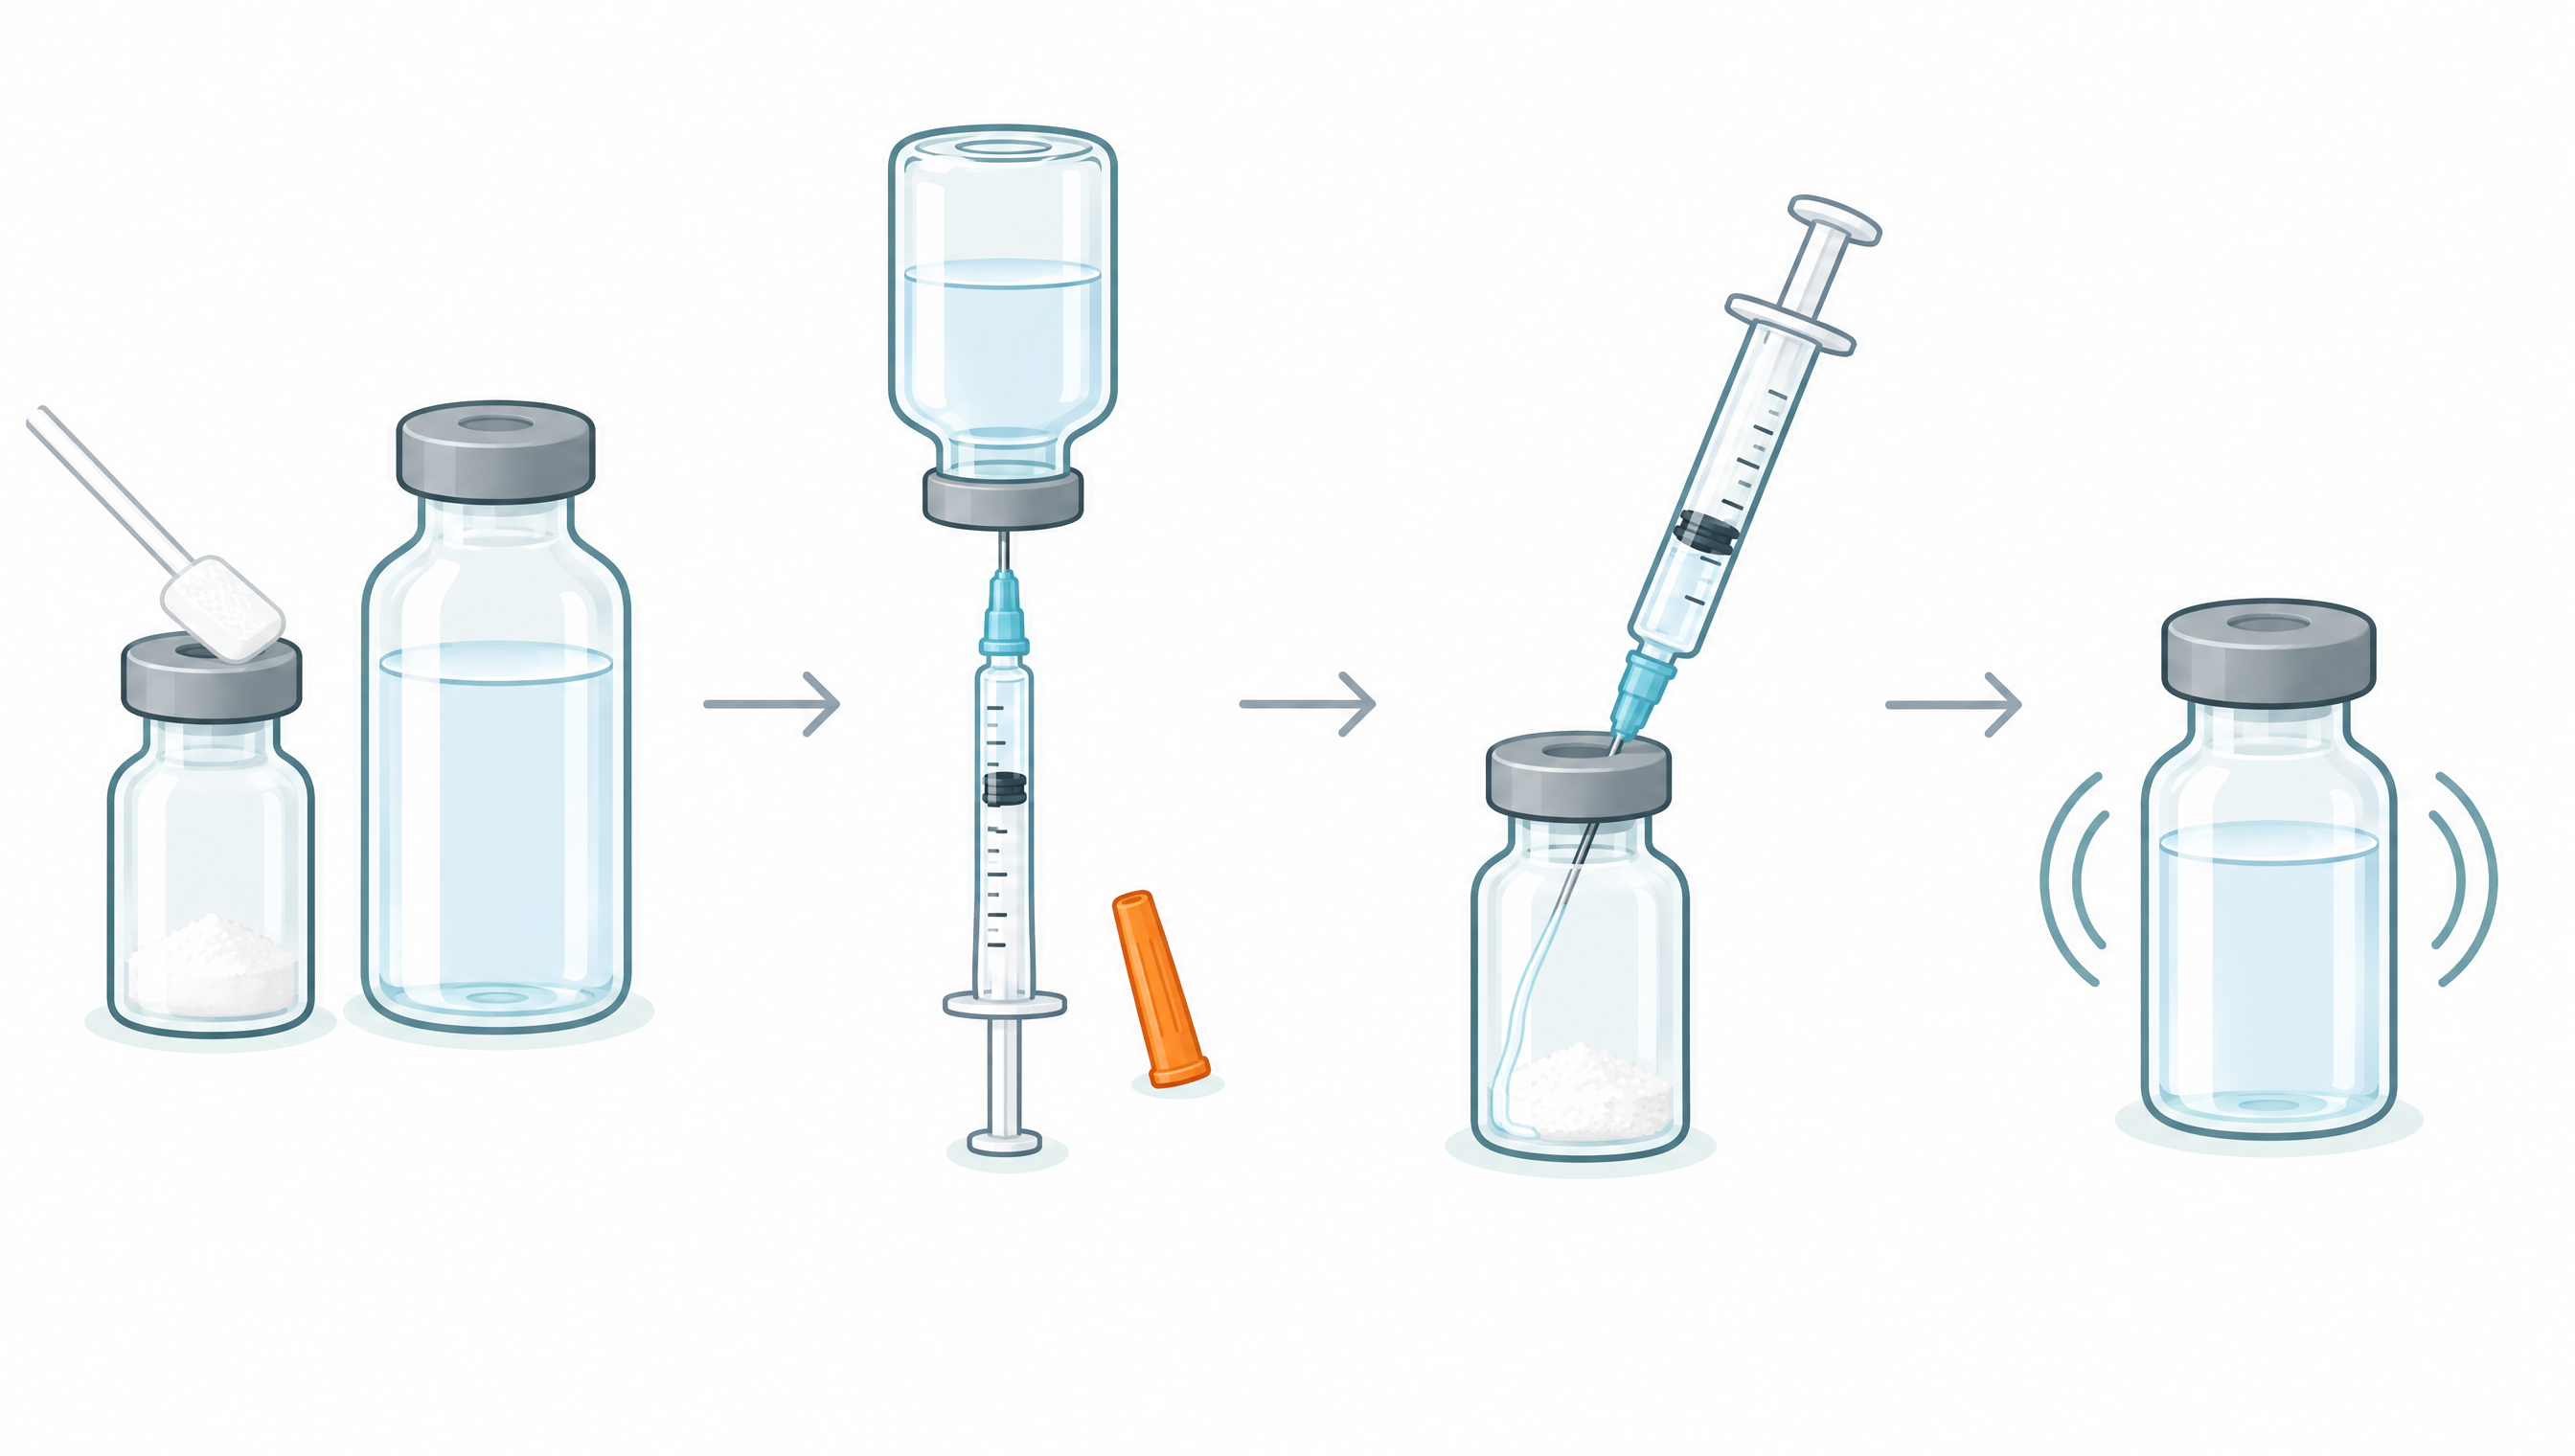
Reconstitution is one calculation chain: concentration (mg/ml) equals vial content (mg) divided by solvent (ml), volume (ml) equals dose (mg) divided by concentration, and units on a U-100 syringe equal volume (ml) times 100.
- Gather materials: the 5 mg + 5 mg vial, bacteriostatic water for injection (USP), U-100 insulin syringes with needles, alcohol swabs and a sharps container. Injection accessories are available in the injection accessories collection.
- Wipe the vial stopper and let the alcohol dry if you use a swab.
- Add 3 ml of bacteriostatic water to the vial (other volumes change the concentration, see the table below).
- Swirl in a circular motion until the powder is fully dissolved. Do not shake.
- Check the solution before use: it should be clear and free of particles or discoloration.
- Draw the dose (for 100 mcg of each peptide: 0.06 ml, 6 units on a U-100 syringe) and label the vial with the date and concentration.
Bacteriostatic water for injection (USP) is sterile water with 0.9 percent (9 mg/ml) benzyl alcohol and comes as a multiple-dose container. Benzyl alcohol solutions are contraindicated in neonates (label). For other vial sizes, use the peptide calculator.
Reconstitution quick reference
With 2, 3 or 5 ml of solvent, 100 mcg of each peptide equals 4, 6 or 10 units on a U-100 syringe.
| BAC water per vial (5 mg + 5 mg) | Concentration per peptide | Volume for 100 mcg | Units on U-100 | Volume for 300 mcg | Units on U-100 |
|---|---|---|---|---|---|
| 2 ml | 2.5 mg/ml | 0.04 ml | 4 units | 0.12 ml | 12 units |
| 3 ml | 1.667 mg/ml | 0.06 ml | 6 units | 0.18 ml | 18 units |
| 5 ml | 1 mg/ml | 0.10 ml | 10 units | 0.30 ml | 30 units |
U-100 example and the U-40 mix-up
On a U-100 syringe, 0.06 ml equals 6 units; reading a U-100 dose on a U-40 scale delivers 2.5 times the intended volume.
| Step | Calculation | Result |
|---|---|---|
| Concentration per peptide | 5 mg / 3 ml | 1.667 mg/ml |
| Volume for 100 mcg | 0.1 mg / 1.667 mg/ml | 0.06 ml |
| Units on U-100 | 0.06 ml x 100 | 6 units |
| Units on U-40 (same volume) | 0.06 ml x 40 | 2.4 units |
On a U-100 syringe one unit is 0.01 ml (100 units per ml), on a U-40 syringe one unit is 0.025 ml (40 units per ml). If you read a U-100 unit count on a U-40 syringe, you deliver 2.5 times the volume; the printed scale (U-40 or U-100) decides, not the cap color. For peptide solutions the marks are a volume scale, so say "units on the syringe", not "IU" (Barrera and Murvelashvili 2019).
Storage after mixing
Use the mixed solution within about four weeks, stored at 2 to 8 °C, according to the supplier; no independent stability data for the blend have been published.
The supplier describes the lyophilized vial as stable at -20 °C for months and advises storing the reconstituted solution at 2 to 8 °C, protected from light, without repeated freezing and thawing (supplier blend guide). The FDA briefing document on ipamorelin (October 29, 2024), citing supplier data, gives a shorter window of 2 to 3 weeks at 4 °C for dissolved ipamorelin. The 28-day rule for multiple-dose containers applies to the opened bacteriostatic water bottle, not to the peptide solution itself (CDC injection safety).
How to inject CJC-1295 and Ipamorelin
Use a short insulin-type syringe, lift a skin fold, inject at 90 degrees to the fold and rotate sites, following insulin injection techniques.
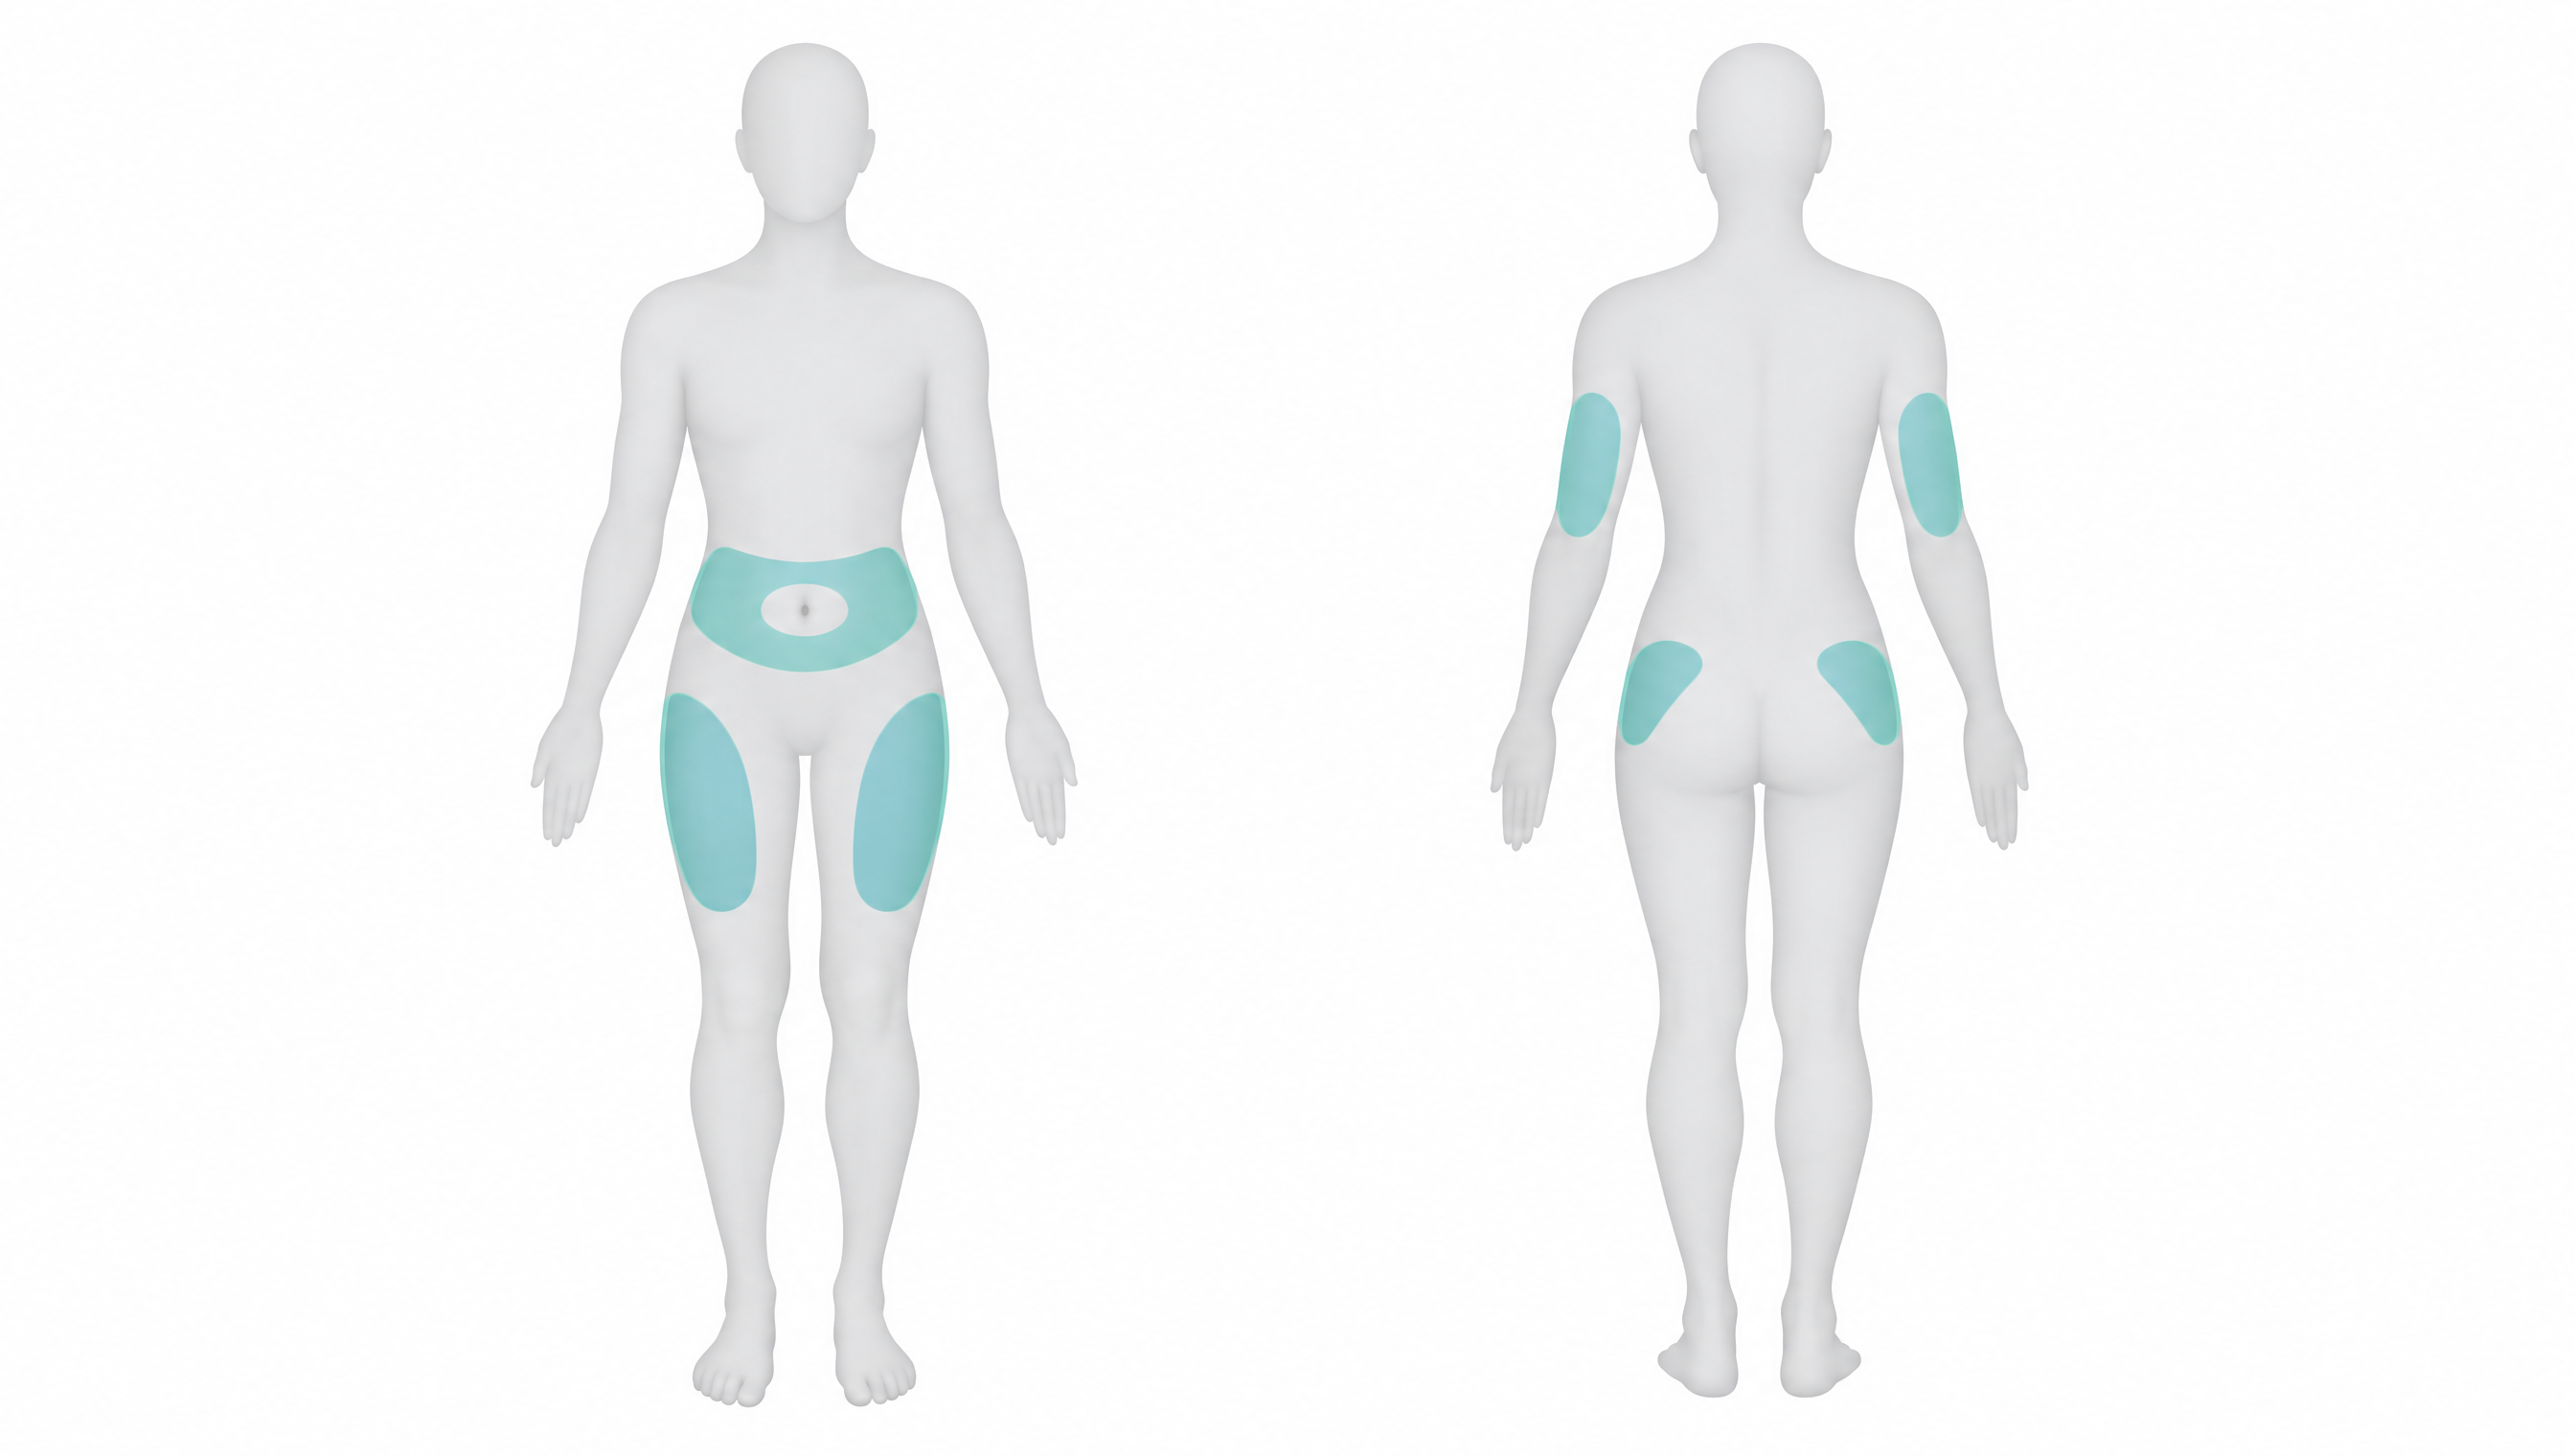
- Wash your hands, clean the skin and let it dry.
- Lift a skin fold, insert the needle at 90 degrees to the fold surface and inject slowly.
- After pressing the plunger fully, keep the needle in the skin for at least 5 seconds (counting to 10 is better), then withdraw it at the same angle and release the fold.
- Change the injection site each time, at least 1 cm away from the previous one; avoid scars, bruises and lipohypertrophy.
- Use a new syringe and needle for every injection, and drop the used needle straight into a puncture-proof sharps container; dispose of it according to local sharps rules.
The technique follows insulin guidelines: the FITTER recommendations (Frid et al. 2016) and the FIT UK injection technique recommendations (5th edition, 2019). Short needles (6 mm syringe needles) are first choice; a skin fold is needed with syringe needles. Syringes and needles are available from the injection supplies collection. Injection sites and needle lengths are covered in more detail in the injection guide.
CJC-1295 and Ipamorelin side effects
No safety study exists for the blend or for CJC-1295 without DAC; in the related CJC-1295-with-DAC study, 94 percent of participants given CJC-1295 (33 of 35) versus 29 percent on placebo reported adverse events after one dose, mostly injection-site reactions (about 70 percent), headache (63 percent) and diarrhea (43 percent).
Most single-dose events were more frequent at the higher doses (125 or 250 µg/kg). With multiple CJC-1295-with-DAC doses, flushing appeared within 30 minutes after injection and settled after 1 to 2 hours, and it was more frequent at the higher dose. The FDA expects a safety profile similar to approved growth hormones, with warnings about neoplasia, glucose intolerance and diabetes; a confirmed clinical carcinogenic signal has not been described. Adverse-event reports for compounded products in the FDA FAERS database are sparse.
| Event | Dose and condition | Rate in the source |
|---|---|---|
| Any adverse event | CJC-1295 with DAC, single dose 30 to 250 µg/kg s.c. | 33 of 35 (94 %) vs 2 of 7 (29 %) placebo |
| Injection-site reactions | same | about 70 % |
| Transient injection-site wheals | same | almost 30 % |
| Headache | same | 63 % vs 14 % placebo |
| Diarrhea | same | 43 % |
| Systemic vasodilation (flush, warmth, brief drop in blood pressure) | same | 30 % |
| Flush within 30 min of injection | CJC-1295 with DAC, multiple doses | 40 % after lower, 100 % after higher dose |
| Nausea or abdominal pain | multiple doses | 20 % |
| Brief dizziness and drop in blood pressure | multiple doses | two participants |
| Increased heart rate | CJC-1295 with DAC, dose-dependent | no rate reported; FDA lists it as a serious event |
| Hypokalemia | ipamorelin 0.03 mg/kg IV twice daily, postoperative | 12.5 % vs 3.4 % placebo |
| Insomnia | same | 10.7 % vs 5.2 % |
| Hyperglycemia at discharge | same | 14.3 % vs 8.6 % |
| Deaths | ipamorelin IV, postoperative after anastomotic leak | two (sepsis, renal failure), relation unclear per FDA |
| Serious adverse events | ipamorelin, Beck 2014 | 17.9 % vs 15.5 % |
| Death after acute myocardial infarction | CJC-1295 with DAC, phase 2 HIV | one participant two hours after the week 11 dose, causality unclear |
| Glucose, liver values, ECG | CJC-1295 with DAC, both studies | no consistent changes |
CJC-1295 and Ipamorelin compared with related peptides
CJC-1295 forms differ from tesamorelin and sermorelin mainly in half-life and evidence level, while ipamorelin acts on a different receptor than all GHRH analogues.
| Compound | Class | Human evidence | Half-life (human) | Status |
|---|---|---|---|---|
| CJC-1295 with DAC | GHRH analogue | phase 1 in 63 healthy volunteers; one phase 2 in HIV patients, terminated 2006 | 5.8 to 8.1 days (estimated) | not FDA or EMA approved |
| CJC-1295 without DAC (Mod GRF 1-29) | GHRH analogue | no reviewed human studies | not reported in humans | not FDA or EMA approved |
| Ipamorelin | ghrelin-receptor agonist | one PK study, two phase 2 (IV) | 2 h after IV infusion | not FDA or EMA approved |
| Sermorelin | GHRH analogue | pediatric program, adult studies | about 4 to 12 minutes depending on the source | US approvals ended 2009 (not for safety or effectiveness reasons) |
| Tesamorelin | GHRH analogue | phase 3 program (HIV lipodystrophy) | 26 min healthy adults, 38 min people with HIV (original EGRIFTA 2 mg); 8 min (SV), 11 min (WR) | FDA-approved (EGRIFTA), never approved in the EU |
Sermorelin vs Ipamorelin vs CJC-1295
Sermorelin is a short-acting GHRH analogue once FDA-approved as GEREF (the manufacturer discontinued it in 2008, and the approvals ended in 2009, not for safety or effectiveness reasons), while ipamorelin is a ghrelin-receptor secretagogue studied only by intravenous infusion.
Structurally, Mod GRF 1-29 (CJC-1295 without DAC) is the GRF(1-29) backbone of sermorelin with four amino-acid exchanges, which slows its enzymatic degradation. In reported use (one protocol website, a forum post and supplier pages), sermorelin appears at 200 to 300 mcg in the evening, while ipamorelin is reported at 100 mcg per injection in blends and at 200 to 300 mcg two to three times daily on its own. Sermorelin plus ipamorelin follows the same GHRH-plus-GHS logic as the blend, but that pairing has not been tested in controlled studies either (Bowers et al. 1990).
CJC-1295 Ipamorelin vs Tesamorelin
Tesamorelin is the only currently FDA-approved GHRH analogue, with phase 3 data in HIV lipodystrophy, while CJC-1295 and ipamorelin have phase 1 and 2 datasets only.
Tesamorelin is a 44-amino-acid GHRH analogue with a hexenoyl residue, approved in the United States since 2010 (EGRIFTA, then EGRIFTA SV and EGRIFTA WR) for excess abdominal fat in HIV lipodystrophy, and never approved in the EU. Its half-life is measured in minutes and depends on the formulation (see the comparison table above), while CJC-1295 with DAC has an estimated half-life of several days. For side-by-side details see the tesamorelin dosing guide.
Ipamorelin alone vs the 1:1 blend
A dose stated for ipamorelin alone cannot be transferred one to one to the blend, because every draw from the blend vial contains both peptides in a 1:1 ratio.
In the 5 mg + 5 mg blend, 100 mcg of each peptide per injection means 200 mcg of total peptide per draw, and vial content and dose always refer to one component. The clinical studies of ipamorelin used the compound alone, by intravenous infusion, at 0.03 mg/kg twice daily up to 0.06 mg/kg three times daily in phase 2; those numbers do not describe a subcutaneous blend schedule. Separate vials follow the same naming: a vial sold as CJC-1295 (Mod GRF 1-29, no DAC) contains the no-DAC form, not the DAC form used in the studies.
Approval status of CJC-1295 and Ipamorelin (2026)
Neither peptide is FDA- or EMA-approved.
In the US, the nominations were withdrawn in 2024, and the Pharmacy Compounding Advisory Committee voted against adding them to the 503A bulks list (ipamorelin free base and acetate, 0 yes to 12 no, on October 29, 2024; the five CJC-1295 substances on December 4, 2024). As of September 2026 the FDA's 503A category list contains neither compound. No FDA-approved product contains either peptide, and there is no USP/NF monograph.
Frequently asked questions
Short answers to the most common search questions about CJC-1295 and ipamorelin.
What is the CJC-1295 and Ipamorelin dosage?
In practice (reported use), 100 mcg of each peptide one to three times daily is the most frequently reported amount, which equals 6 units on a U-100 syringe per injection when a 5 mg + 5 mg vial is mixed with 3 ml. No study tested the blend: human studies gave CJC-1295 with DAC as single injections or every 1 to 2 weeks at 20 to 250 µg/kg (1.4 to 17.5 mg at 70 kg), or ipamorelin intravenously.
How much CJC-1295 and Ipamorelin per day?
The most commonly reported pattern is 100 mcg of each peptide one to three times daily, i.e. 100 to 300 mcg of each per day (200 to 600 mcg total peptide). Supplier and dosing pages list 100 to 300 mcg per peptide once or twice daily, and single forum users report up to 500 mcg CJC-1295 and 1 mg ipamorelin. No trial has established a daily target.
What is the difference between CJC-1295 with DAC and without DAC?
They are two different, non-interchangeable substances. With DAC, the estimated half-life is 5.8 to 8.1 days and every human study used that form; without DAC (Mod GRF 1-29) no human half-life has been reported and no controlled human study exists. Shops usually sell the no-DAC form as CJC-1295.
How long does mixed CJC-1295 and ipamorelin last in the fridge?
The supplier advises using the reconstituted solution within about four weeks, stored at 2 to 8 °C; the FDA briefing document on ipamorelin, citing supplier data, gives a shorter window of 2 to 3 weeks for the dissolved peptide. No independent stability data for the blend have been published. The 28-day rule for multi-dose containers applies to the opened bacteriostatic water bottle, not to the peptide solution.
When should you inject CJC-1295 and Ipamorelin?
Reported patterns are one evening injection (one user describes this fasted on 5 of 7 days) or a split schedule in the morning and before bed. No study has compared timing or tested whether fasting changes the GH response, so the choice follows practice convention rather than evidence.
Can CJC-1295 with DAC be swapped for the no-DAC form?
No. The two forms are different substances with different dosing patterns. A 2026 review of forum reports lists CJC-1295 with DAC at 1 to 2 mg per week in one or two injections, while the no-DAC form (Mod GRF 1-29) appears at 100 to 200 mcg per injection once or twice daily. A schedule for one form cannot be applied to a vial of the other.
CJC-1295 Ipamorelin vs Tesamorelin: which is better studied?
Tesamorelin is better studied: it is the GHRH analogue with a current FDA approval (HIV lipodystrophy) and phase 3 data. CJC-1295 and ipamorelin have only small phase 1 and 2 datasets. Which one is better outside approved use cannot be answered from the available data.
What side effects can CJC-1295 and Ipamorelin cause?
In the single-dose CJC-1295-with-DAC study, 94 percent reported any adverse event: injection-site reactions about 70 percent, headache 63 percent, diarrhea 43 percent, systemic vasodilation such as flushing or warmth 30 percent. After bowel surgery, intravenous ipamorelin was linked to more hypokalemia (12.5 versus 3.4 percent) and insomnia (10.7 versus 5.2 percent) than placebo. No safety study exists for the blend itself.
Does the CJC-1295 Ipamorelin blend build muscle?
This has not been studied. No controlled trial measured muscle mass or strength with the blend or with CJC-1295 without DAC; the measured human outcomes are GH and IGF-1 increases under CJC-1295 with DAC. Muscle-growth claims are therefore not supported by clinical data.
What are the benefits of CJC-1295 and Ipamorelin?
Documented effects are hormonal: CJC-1295 with DAC raised GH 2- to 10-fold and IGF-1 1.5- to 3-fold for days to weeks, while pulses stayed intact. Outcomes such as fat loss, sleep or recovery are not established in controlled studies.
What do CJC-1295 ipamorelin user reports in forums describe?
In bodybuilding forums such as ExcelMale and TMuscle, reports cluster at 100 mcg of each peptide one to three times daily, sometimes 5 days on and 2 days off. They are anecdotal. One AnabolicMinds thread reports IGF-1 rising from 227 to 406 ng/ml, but the baseline value was four years old and other compounds were used in parallel.
How long does a 5 mg + 5 mg vial last?
A 5 mg + 5 mg vial holds 50 draws of 100 mcg per peptide, so it lasts about 17 days at three injections per day. At one injection daily, the supplier's four-week window at 2 to 8 °C ends after about 28 of the 50 draws.
Sources
Studies, registers and authority documents cited in this guide.
- FDA CDER. Briefing Document, Pharmacy Compounding Advisory Committee, December 4, 2024: CJC-1295-Related Bulk Drug Substances.
- FDA CDER. Briefing Document, Pharmacy Compounding Advisory Committee, October 29, 2024: Ipamorelin-Related Bulk Drug Substances.
- Jette L et al. Human growth hormone-releasing factor (hGRF)1-29-albumin bioconjugates activate the GRF receptor: identification of CJC-1295. Endocrinology. 2005.
- Raun K et al. Ipamorelin, the first selective growth hormone secretagogue. European Journal of Endocrinology. 1998.
- Frohman LA et al. Rapid enzymatic degradation of growth hormone-releasing hormone by plasma. Journal of Clinical Investigation. 1986.
- Soule S et al. Incorporation of D-Ala2 in growth hormone-releasing hormone-(1-29)-NH2 increases the half-life and decreases metabolic clearance in normal men. Journal of Clinical Endocrinology and Metabolism. 1994.
- Bowers CY et al. Growth hormone (GH)-releasing peptide stimulates GH release in normal men and acts synergistically with GH-releasing hormone. Journal of Clinical Endocrinology and Metabolism. 1990.
- Teichman SL et al. Prolonged stimulation of growth hormone (GH) and insulin-like growth factor I secretion by CJC-1295. Journal of Clinical Endocrinology and Metabolism. 2006.
- Ionescu M, Frohman LA. Pulsatile secretion of growth hormone (GH) persists during continuous stimulation by CJC-1295. Journal of Clinical Endocrinology and Metabolism. 2006.
- Sackmann-Sala L et al. Activation of the GH/IGF-1 axis by CJC-1295, a long-acting GHRH analog, results in serum protein profile changes in normal adult subjects. Growth Hormone & IGF Research. 2009.
- ConjuChem. ClinicalTrials.gov NCT00267527, CJC-1295 in HIV patients with visceral obesity (terminated).
- Gobburu JV et al. Pharmacokinetic-pharmacodynamic modeling of ipamorelin in human volunteers. Pharmaceutical Research. 1999.
- Beck DE et al. Prospective, randomized, controlled study of the ghrelin mimetic ipamorelin for postoperative ileus in bowel resection patients. International Journal of Colorectal Disease. 2014.
- Helsinn Therapeutics. ClinicalTrials.gov NCT01280344, ipamorelin compared with placebo after bowel resection.
- Dominikowski A et al. The emerging landscape of performance-enhancing peptides modulating the GH-IGF1 axis. Frontiers in Endocrinology. 2026.
- TMuscle forum. Mod GRF 1-29 and ipamorelin dosing, timings and cycling. 2014.
- ExcelMale forum. How many times per day do you dose your ipamorelin and Mod GRF 1-29. 2020.
- ExcelMale forum. How to start and mix on ipamorelin and Mod GRF1-29. 2022.
- AnabolicMinds forum. Single IGF-1 report with Mod GRF 1-29 and ipamorelin. 2022.
- Peptide Critic community. CJC1295 + Ipamorelin protocol thread. 2026.
- BergdorfBio. CJC-1295 (no DAC) peptide calculator (German-language page). 2026.
- BergdorfBio. Ipamorelin calculator. 2026.
- BergdorfBio. CJC-1295 and Ipamorelin blend guide (German-language page). 2026.
- PeptideDosages.com. CJC-1295 no DAC + Ipamorelin 10 mg blend dosage protocol. Updated September 20, 2026.
- Barrera F, Murvelashvili N. Poorly controlled type 3c diabetes due to use of veterinarian insulin syringes (U-100 and U-40 scales). Case Reports in Endocrinology. 2019.
- FDA. Bulk Drug Substances Nominated for Use in Compounding Under Section 503A (category update, September 29, 2023).
- FDA. Bulk drug substances used in compounding (category list updated May 14, 2026).
- FDA. Certain bulk drug substances for use in compounding that may present significant safety risks (Category 2) (content current as of April 22, 2026).
- FDA CDER. Final Summary Minutes of the Pharmacy Compounding Advisory Committee Meeting, October 29, 2024.
- FDA CDER. Minutes of the Pharmacy Compounding Advisory Committee Meeting, December 4, 2024.
- Hospira (Pfizer). Bacteriostatic Water for Injection, USP (DailyMed label).
- Centers for Disease Control and Prevention. Preventing unsafe injection practices.
- Frid AH et al. New insulin delivery recommendations (FITTER). Mayo Clinic Proceedings. 2016.
- Forum for Injection Technique (FIT) UK. The UK injection and infusion technique recommendations, 5th edition. 2019.
- FDA. Best way to get rid of used needles and other sharps.
- FDA, HHS. Determination that GEREF (sermorelin acetate) injection was not withdrawn from sale for reasons of safety or effectiveness. Federal Register. 2013.
- Theratechnologies. EGRIFTA (tesamorelin) prescribing information (2010; EGRIFTA SV 2024; EGRIFTA WR 2025).
- European Medicines Agency. Withdrawal of the marketing authorisation application for Egrifta (tesamorelin). 2012.
